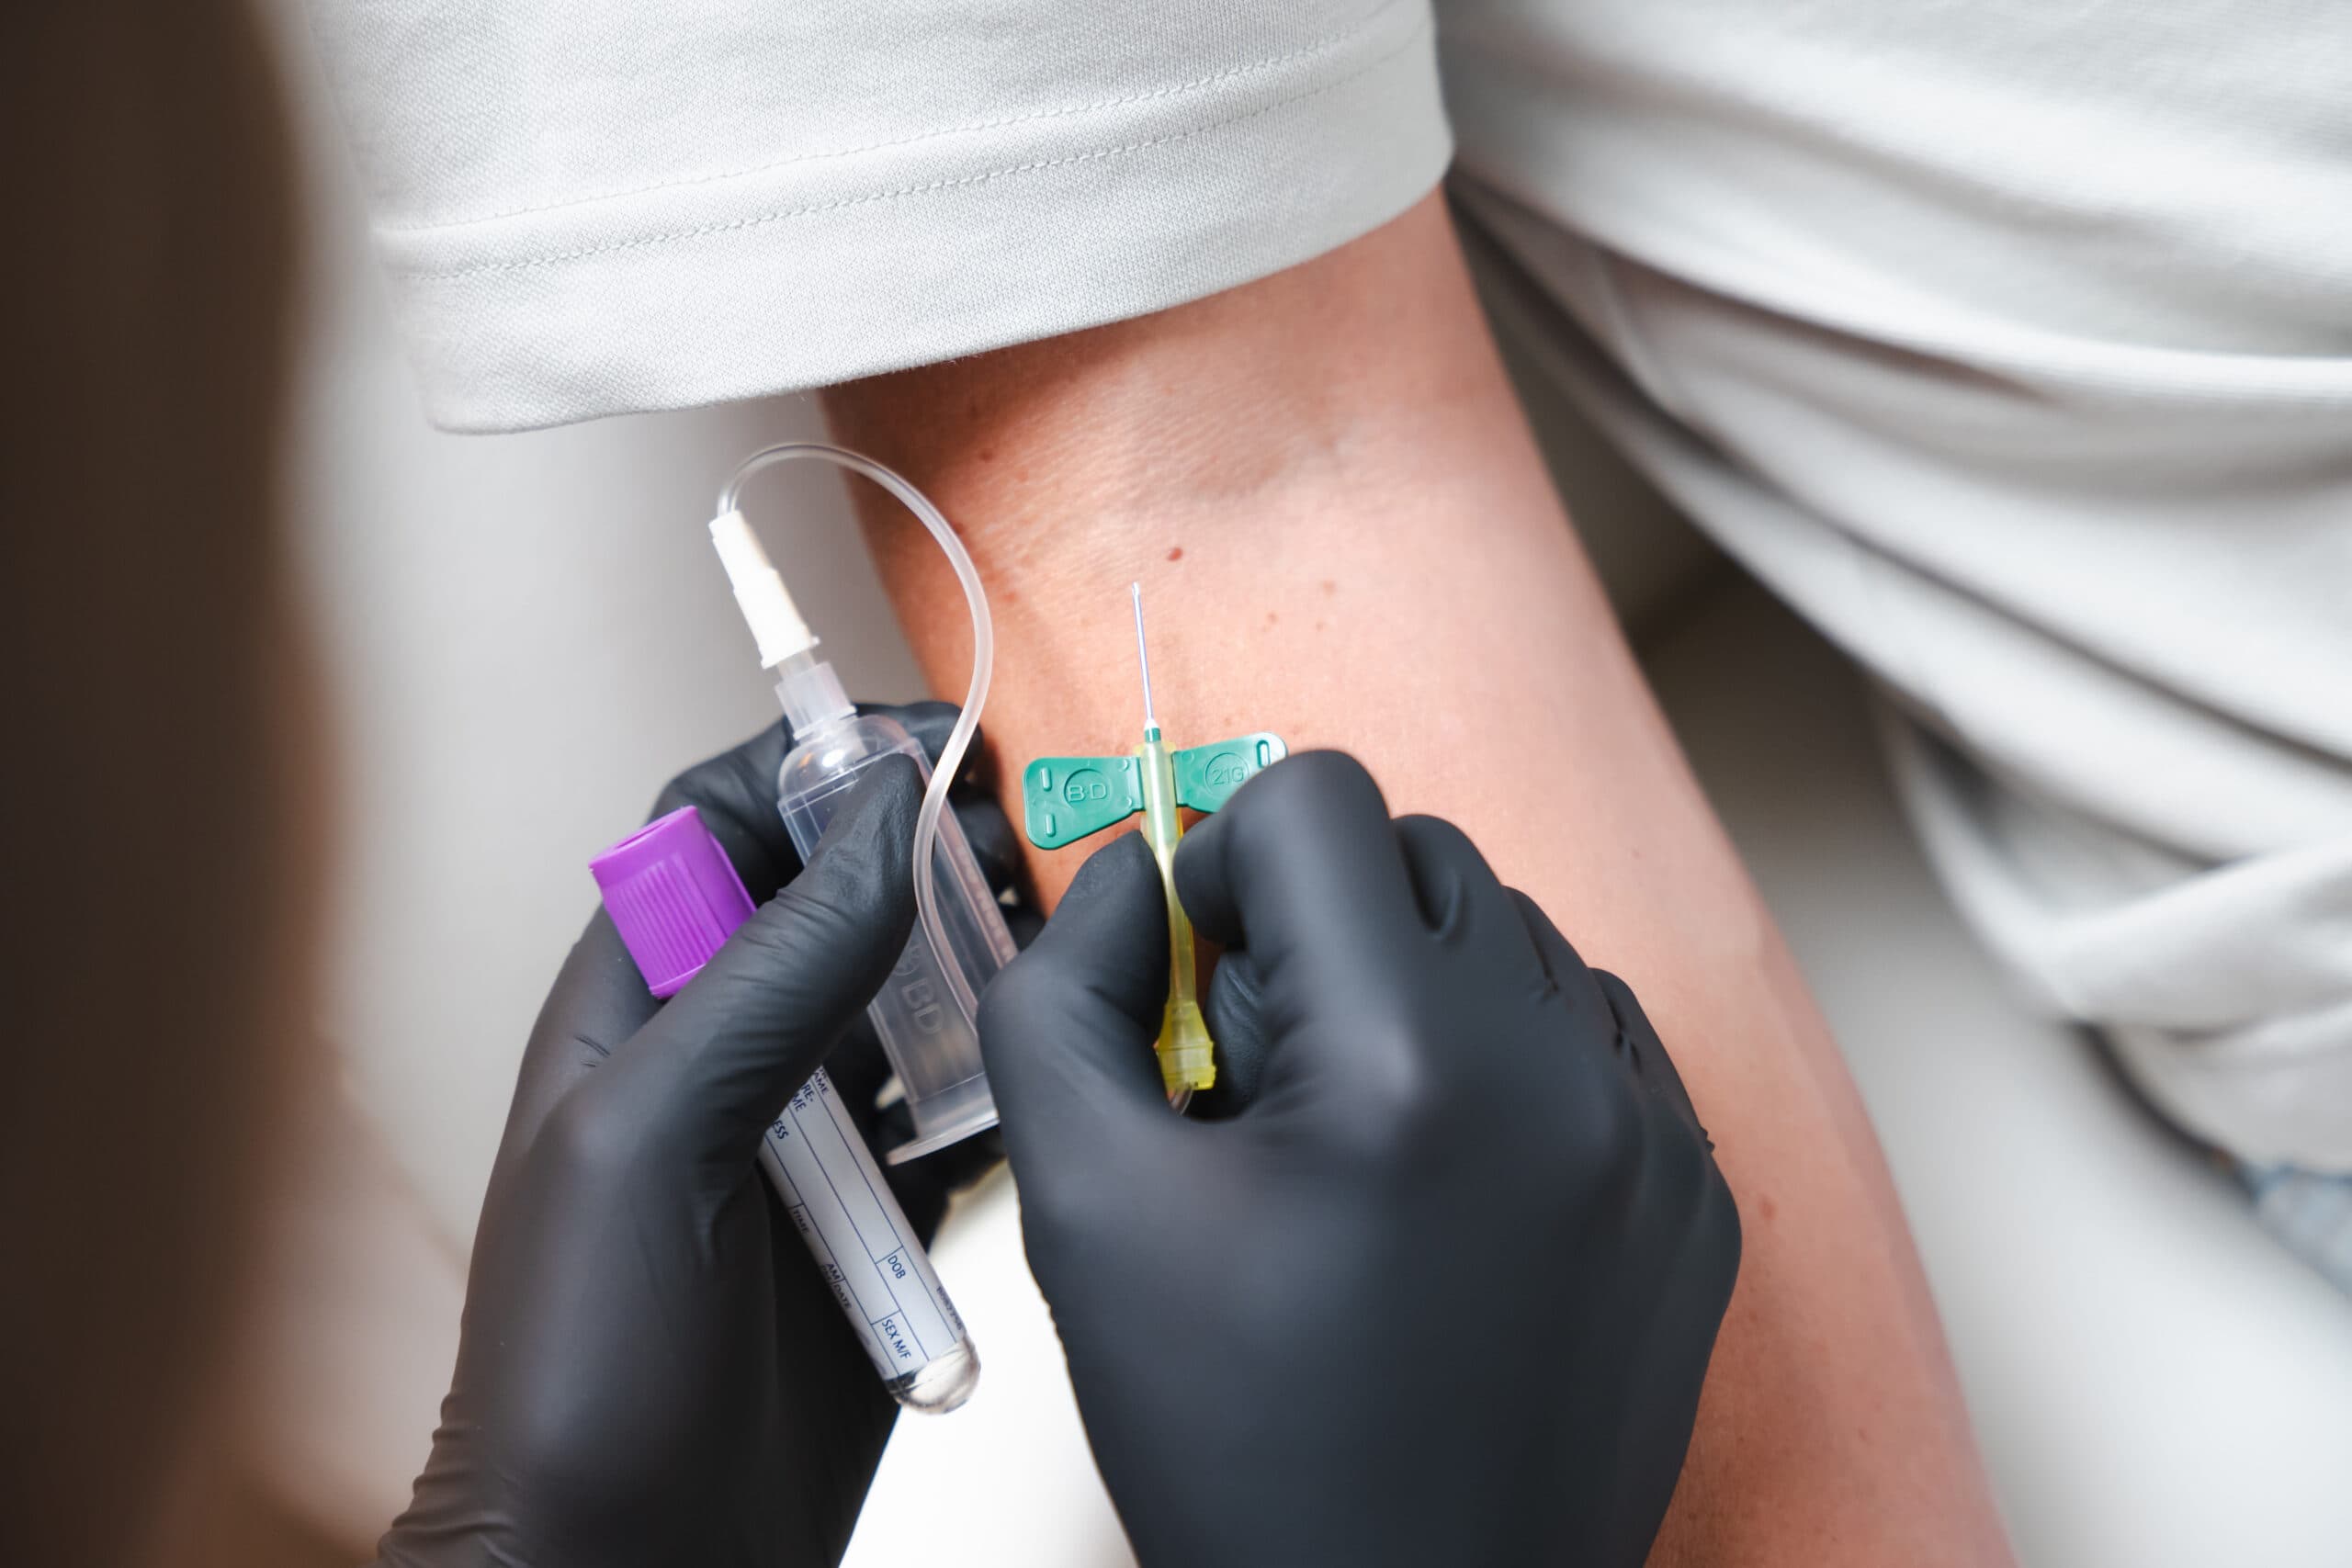
Every winter, drips and injections are marketed as a way to recover from illness, lift your energy and boost your immune system. Some of these treatments help a lot, but only for the right person. Others have far less evidence behind them than the marketing suggests. At The Wright Practice, we explain what NAD+, glutathione, vitamin infusions, B12 and iron treatments actually do, who may benefit, and why a proper assessment comes first.
A few quick answers before we go into more detail.
The table below sets out what each treatment is used for and how strong the evidence is, so you can see the differences at a glance.
| Treatment | What it is used for | How strong is the evidence? | Who it may suit |
|---|---|---|---|
NAD+ infusion | Supporting energy and recovery as part of a wider plan | Early. Mostly small studies, not yet standard care | Selected patients who understand the limits, after other causes are assessed |
Glutathione | Antioxidant support | Limited for healthy people. Not shown to boost immunity | Individual decisions only, after discussion of the evidence |
Vitamin and micronutrient infusion | Replacing nutrients that are low or poorly absorbed | Good when a deficiency is confirmed. Weak for general wellness | People with a confirmed deficiency or absorption problem |
B12 injection | Treating vitamin B12 deficiency | Strong for confirmed deficiency. No benefit shown for energy if levels are normal | People with low B12, especially if tablets are unsuitable |
IV iron | Replacing iron when stores are low | Strong in the right patients, usually after tablets have failed or are not tolerated | People with confirmed iron deficiency |
It depends on why you feel run down. If low iron, low B12 or poor absorption is behind your tiredness, correcting it can make a real difference. If your tiredness comes from poor sleep, stress, an underactive thyroid or a lingering infection, an infusion will not fix it.
That is why we treat these as targeted treatments rather than winter pick-me-ups. They do not protect you from colds, flu or COVID-19. Vaccination, sleep, food and investigating symptoms properly remain the foundations.

NAD+ is a molecule found in every cell. It helps turn food into energy and supports cell repair. Levels fall with age, which has driven interest in replacing it through infusions.
It is worth being straightforward. Human research on intravenous NAD+ is still early, and most studies are small. Some patients report feeling more energised, but this is not yet guideline-backed care. Our blog on NAD+ IV therapy: what it is and what to expect covers how a session works in more detail.

No. Glutathione is an antioxidant your body makes naturally, and it plays a part in normal immune function. But there is not enough good evidence that giving it by drip boosts immunity, energy or general wellness in healthy people.
Where it is used, it is usually as one ingredient in a nutrient formulation, and it is discussed individually with a clinician. Product quality and medical supervision matter, because unregulated injectable products carry real risks.
B12 injections are for treating a confirmed B12 deficiency. In the UK, the usual treatment is an injection of hydroxocobalamin when the cause is poor absorption, as in pernicious anaemia, or when there are nerve symptoms. If low B12 is simply due to diet, tablets are often enough.
Most people with normal B12 levels see no benefit in energy from an injection, which is why the first step is a blood test.


Iron deficiency is a common cause of tiredness, breathlessness and hair shedding, particularly in women with heavy periods. A ferritin level below about 30 micrograms per litre generally points to iron deficiency, although higher cut-offs apply when there is inflammation.
Iron tablets are normally the first treatment. IV iron is usually considered when tablets are not tolerated, do not work, are poorly absorbed, or when faster replacement is needed. It is just as important to ask why iron is low, since blood loss from the gut or heavy periods may need investigating.
You can read more about this on our page for private iron infusions in London.
“Infusions are useful tools, but only when they are used for the right reason,” says Dr Dan Wright. “I would rather test first and treat a genuine deficiency than sell a drip to someone whose tiredness has another cause. If an infusion will not help you, I will tell you.”
This careful approach runs across every consultation at our Harley Street clinic.

Yes. Flu viruses change from year to year, and vaccines are updated to match, so protection from last year’s flu vaccine will not cover this winter. If you are eligible, an annual flu vaccine is recommended each autumn.
Usually, yes. Both can be given at one appointment, which many people find convenient. You may feel slightly more tired or have a sorer arm, but this normally settles within a day or two.
The NHS offers the RSV vaccine to pregnant women, adults aged 75 and over, adults aged 65 to 74 with a weakened immune system or long-term lung condition, and older care home residents. If you are outside these groups, a review at The Wright Practice can discuss whether vaccination is appropriate.
No. The pneumococcal vaccine is usually a single dose rather than a yearly one. It is offered to adults aged 65 and over, and to some younger adults with certain long-term conditions.
The NHS shingles vaccine is given as two doses, usually six to twelve months apart. It is offered to adults turning 65, to those aged 70 to 79 who have not yet had it, and to adults with a severely weakened immune system.
Yes. You can get shingles more than once, so vaccination is still worthwhile if you are eligible. Your clinician will usually advise waiting until the rash has fully cleared.
For most people, yes. Some medicines, such as steroids or immune-suppressing treatments, change which vaccines are recommended and when. Tell your clinician at The Wright Practice about everything you take so they can advise correctly.
Start by checking your NHS App or GP records, which often show your vaccination history. If gaps remain, a consultation at The Wright Practice can help you piece together what you have had and what may be worth catching up on.
No. The NHS flu programme runs until 31 March 2027, and a late vaccine still offers protection against flu that circulates later in winter. Earlier is better, but a later dose is worth having if you are eligible.
Not quite. Protection takes up to two weeks to build after flu vaccination, so it is sensible to be vaccinated before winter illnesses are widespread. Vaccines reduce your risk of serious illness but cannot guarantee you will avoid infection.
Knowing which winter vaccines you actually need is more useful than having every one on offer. Book a consultation with The Wright Practice today to review your records and plan your protection.
Rated ★ ★ ★ ★ ★ from 197 Reviews


